Repeated urinary infections in a man can result from incomplete bladder emptying, but an enlarged prostate is only one possible cause. You will be able to identify the tests that link infection to obstruction, recognise when laser surgery is reasonable, and know which symptoms after surgery require prompt assessment.
Key takeaways
- Two culture-confirmed UTIs in six months meet the usual recurrent-UTI definition.
- Measure post-void residual urine to check whether the bladder empties fully.
- Laser surgery helps when obstruction and retained urine drive repeated infections.
- Fever after prostate surgery needs prompt medical assessment, not self-treatment.
When do repeated urinary infections point to a prostate problem?
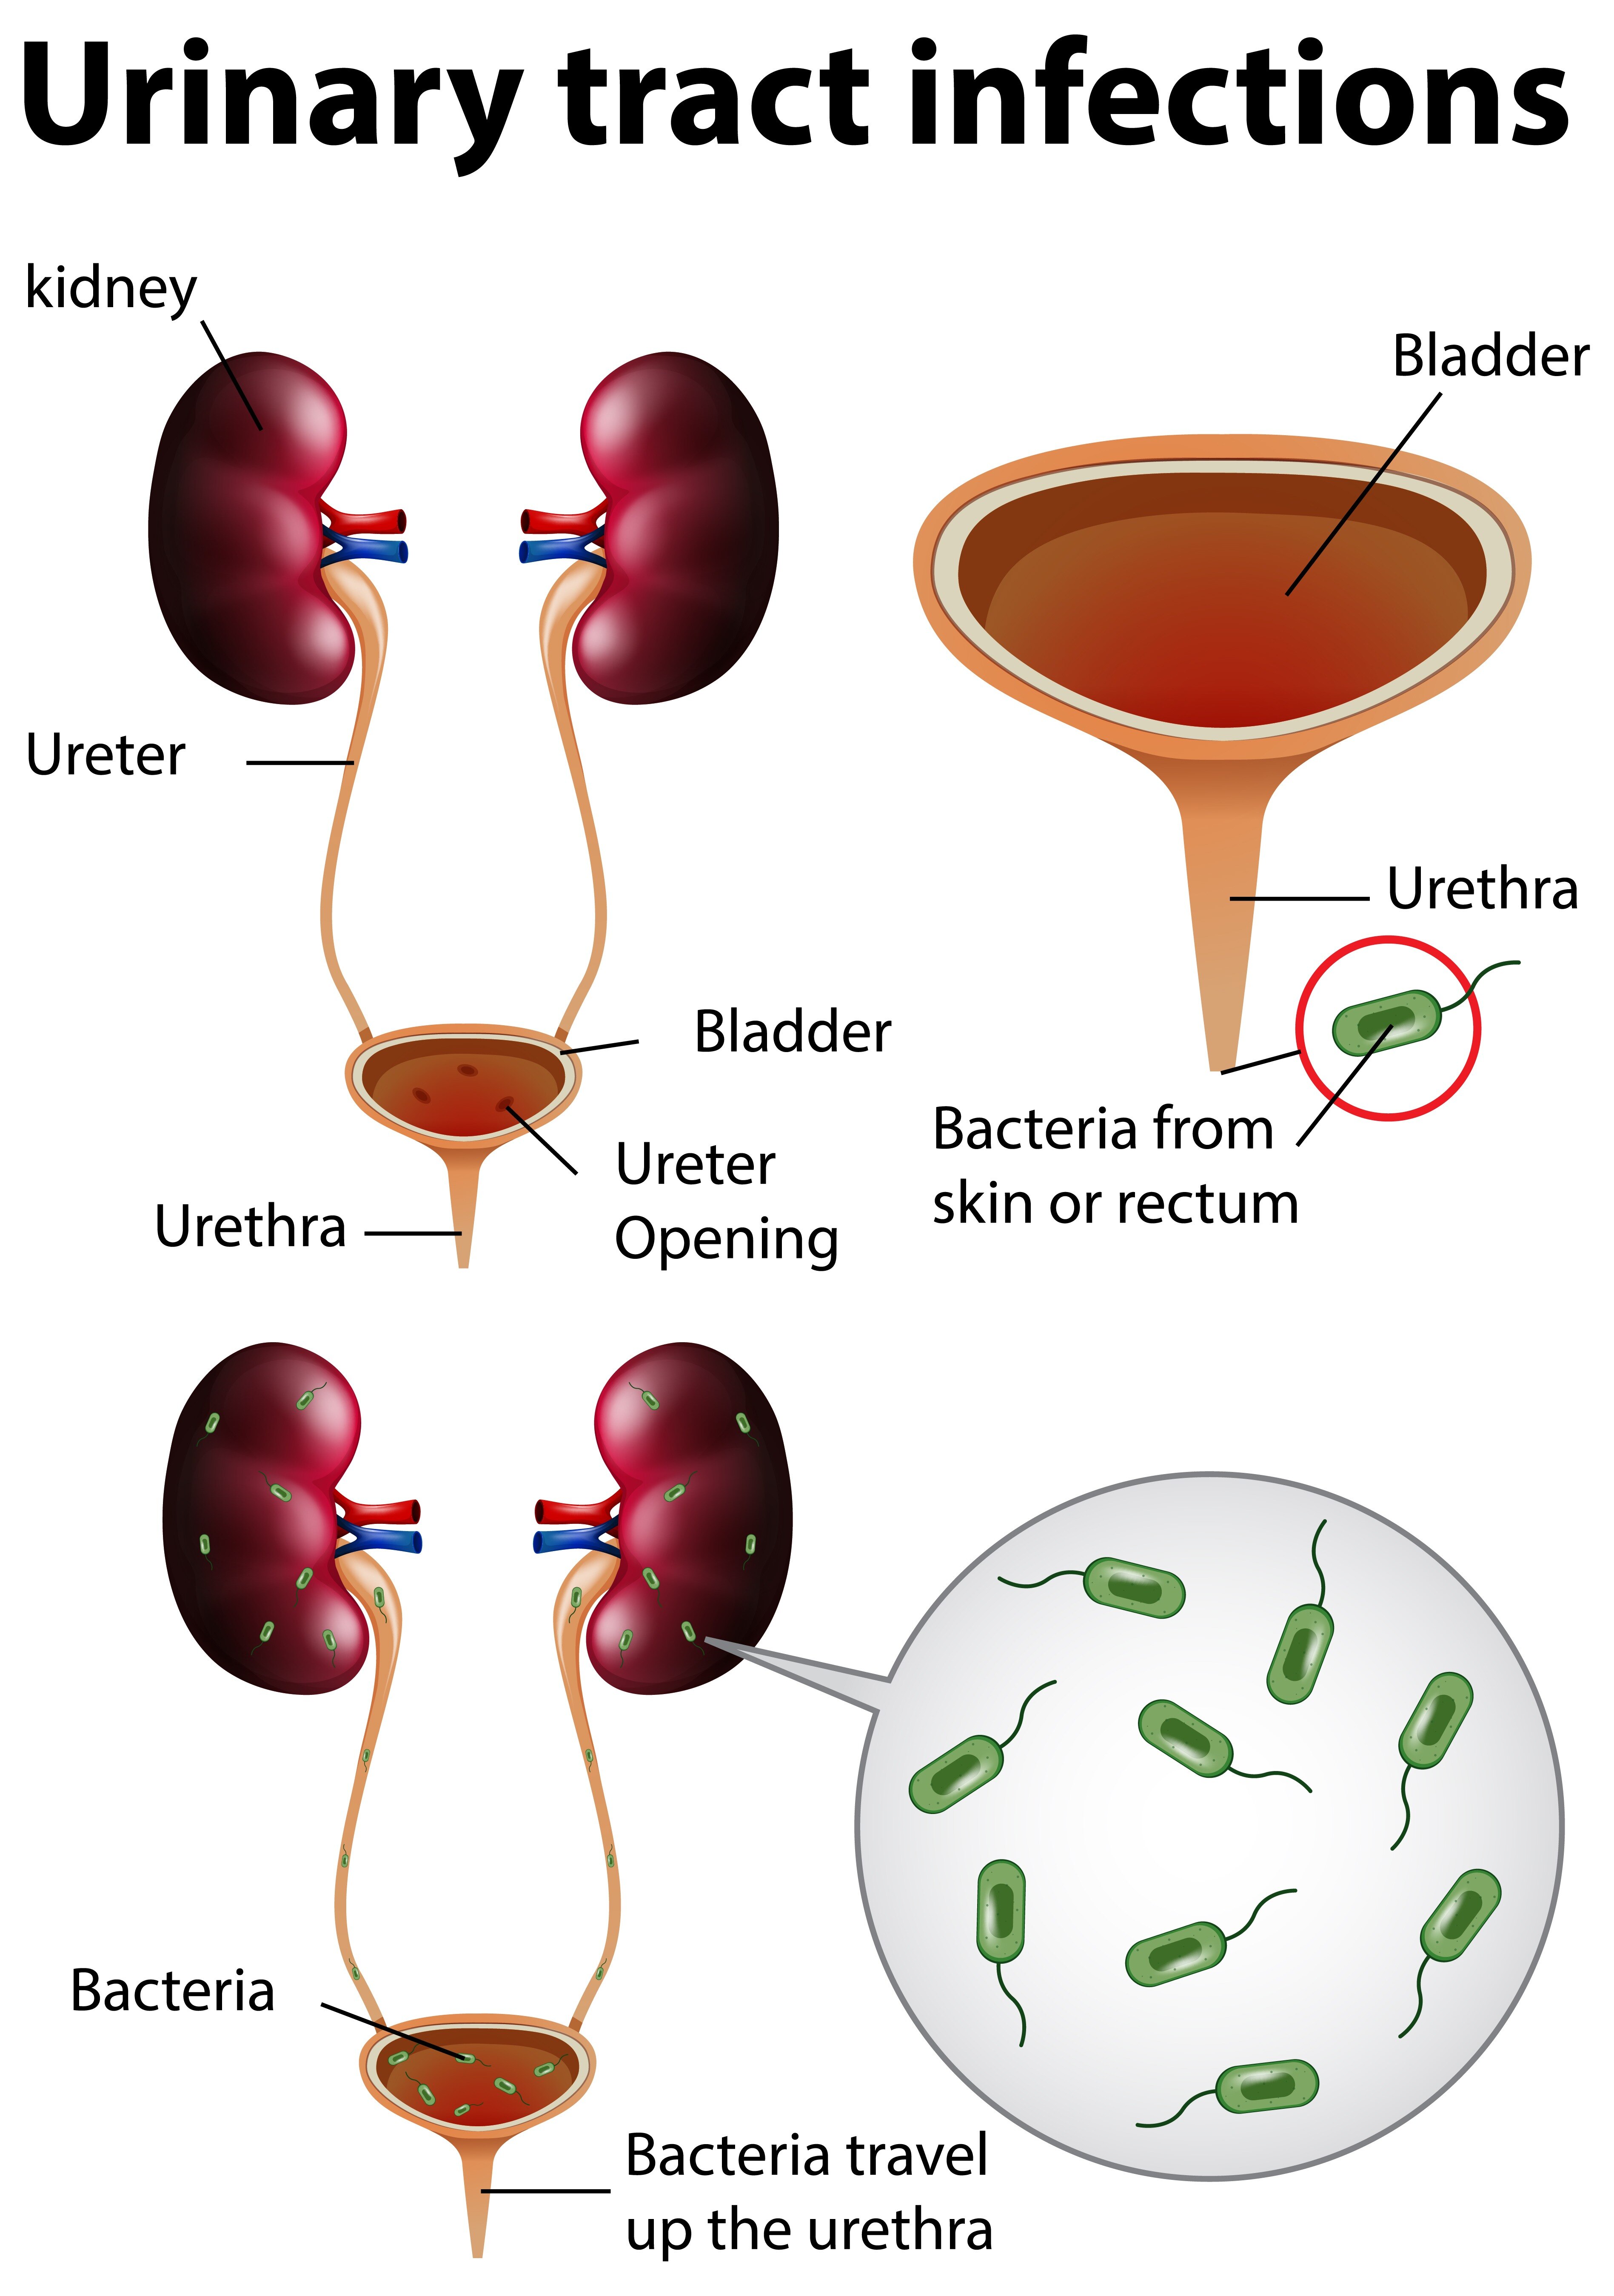
Two symptomatic, culture-confirmed infections within six months, or three within 12 months, meet the usual definition of recurrent urinary tract infections. In men, urinary retention from bladder outlet obstruction can leave residual urine behind; that stagnant urine can become infected and repeatedly seed the bladder.
Bacterial prostatitis can also shelter bacteria in prostate tissue and cause relapsing infections. This is how recurrent urinary tract infections and prostate problems can be connected.
Before blaming an enlarged prostate, separate a true recurrence from similar symptoms:
- Persistent infection: the original organism was never cleared, so symptoms or cultures return soon after treatment.
- Contaminated sample: skin bacteria or poor collection produces a misleading culture.
- Overactive bladder: urgency and frequency occur without bacterial growth.
- Sexually transmitted infection: urethral burning or discharge requires STI testing, not simply prostate treatment.
- Bladder stones: bacteria can persist on the stone’s surface.
- Urethral stricture: narrowing slows flow and prevents complete emptying.
- Prostate-related symptoms: enlargement or inflammation can cause urgency, weak flow, burning, or hesitancy without infection.
A positive dipstick alone does not prove the cause. Ask for a properly collected urine culture with antibiotic sensitivity, and have post-void residual urine measured. Repeated matching cultures, incomplete emptying, weak flow, or retention strengthen the case for obstruction or prostatitis; normal cultures point elsewhere.
Which tests show whether the prostate is causing the infections?
No single test proves that the prostate is causing repeated infections. Before considering prostate laser surgery for recurring urinary tract infections, evaluate the urine, bladder emptying, urinary flow, kidneys, bladder, urethra and prostate.
| Test | What it shows | Why it matters |
|---|---|---|
| Urinalysis | Blood, white cells and bacteria indicators | Supports inflammation or infection, but a positive dipstick alone does not identify the cause |
| Urine culture with antibiotic sensitivity | The organism and medicines likely to treat it | A stable patient should give the sample before antibiotics; the result guides targeted treatment |
| Post-void residual measurement | Urine left after urination | A high residual confirms incomplete emptying, not that the prostate caused it |
| Uroflowmetry | Flow rate and pattern | Weak flow supports obstruction but cannot distinguish prostate blockage from poor bladder contraction |
| Kidney and bladder imaging | Stones, swelling, bladder changes or retained urine | Finds infected stones and upper-tract problems that surgery would not fix |
| Prostate assessment | Size, consistency, PSA and rectal-examination findings | An unexplained PSA rise or abnormal examination requires cancer assessment |
| Cystoscopy when indicated | Direct view of the urethra and bladder | Detects urethral narrowing, stones, tumours or another blockage |
A high residual can result from weak bladder contraction, neurologic disease, medication effects or urethral narrowing. When flow is poor but the cause remains unclear, pressure-flow testing measures bladder strength and outlet resistance, preventing prostate surgery for the wrong problem.
Before elective surgery, identify and treat active infection. A culture also helps distinguish persistent infection from contamination or unrelated urinary symptoms.
When can laser surgery reduce the risk of another infection?
Laser surgery is rational when recurrent, culture-confirmed infections occur alongside incomplete emptying caused by benign prostatic obstruction. The American Urological Association recognises recurrent UTI caused by BPH obstruction as an indication for surgery.
Use this decision check:
1. Confirm the link: raised post-void residual urine, weak flow, straining, urgency, or recurrent retention must match the obstructing prostate findings. Treat an active infection and obtain a urine culture before surgery; operating through untreated infection raises sepsis risk.
2. Reject the wrong target: infection with normal residual urine, untreated prostatitis, weak bladder contraction, bladder dysfunction, an unaddressed infected stone, or urethral stricture needs another solution. Prostate laser surgery for recurring urinary tract infections does not sterilise the urinary tract or reliably cure bacterial prostatitis.
3. Assess cancer risk first: an unexplained PSA rise or abnormal rectal examination requires prostate-cancer assessment before choosing a tissue-destroying procedure.
4. Compare the procedure with your anatomy, bleeding risk, anticoagulant plan, and surgeon’s experience:
| Option | Tissue for histopathology | Selection considerations |
|---|---|---|
| HoLEP | Usually provides enucleated tissue | Suits a broad prostate-size range; useful when tissue diagnosis matters |
| ThuLEP | Usually provides enucleated tissue | Similar size and anatomy decisions depend on equipment and expertise |
| GreenLight/PVP | Little or no tissue specimen | Vaporisation can suit selected anatomy and bleeding concerns; discuss cancer assessment and anticoagulants beforehand |
The realistic goal is better emptying, not a guarantee against future UTIs. At VANDANA URO CARE in Pune, you can review cultures, residual-volume measurements, prostate findings, and procedure selection with a urology specialist.
Related service
Prostate Laser Surgery Prostate laser surgery is used to relieve moderate to severe urinary symptoms caused by an enlarged prostate — a condition known as benign prostatic... View service → |
What changes when chronic bacterial prostatitis is the suspected source?
Repeated culture-confirmed infections that return after treatment raise a different question: is bacteria persisting in the prostate? Chronic bacterial prostatitis becomes more likely when symptoms relapse, pelvic or perineal discomfort continues, or cultures repeatedly identify the same organism. This pattern points toward prostate problems, not automatically an enlarged prostate.
A clinician may investigate the suspected source by:
- Obtaining a urine culture with antibiotic sensitivity before treatment when you are stable.
- Comparing pre-treatment and post-treatment cultures, and using clinician-directed prostate localisation testing when appropriate.
- Reviewing antibiotic exposure, sexually transmitted infection risk, urinary retention, stones, and prior instrumentation.
- Checking prostate findings, post-void residual urine, urinary flow, and imaging when obstruction or another urinary source is possible.
A positive dipstick or urinary burning alone cannot establish prostatitis. Burning can come from urethral irritation, overactive bladder, stones, sexually transmitted infection, or recent catheterisation.
HoLEP, ThuLEP, and GreenLight/PVP relieve bladder-outlet obstruction; they do not sterilise the urinary tract or reliably cure chronic bacterial prostatitis. If the prostate is infected, culture-guided antimicrobial treatment and specialist evaluation remain necessary. Surgery addresses obstruction separately, particularly when residual urine coexists; it is not a substitute for treating the infected prostate.
How should you manage recovery and a urinary infection after prostate surgery?
The key prostate laser surgery recovery tips are to drink enough fluid to keep urine flowing unless you have a fluid restriction, take prescribed medicines exactly as directed, avoid heavy lifting and strenuous activity until cleared, and prevent constipation with fluids, fibre, and any recommended stool softener.
Frequency, urgency, burning, small amounts of blood, and occasional leakage are common while the bladder and urethra settle. These symptoms alone do not prove a urinary infection after prostate surgery, especially after catheterisation or other instrumentation; postoperative inflammation, retention, and catheter irritation can look similar.
A urine culture with antibiotic sensitivity is more reliable than symptoms, so do not self-start leftover antibiotics.
Follow these safety rules:
- Contact your surgical team promptly if burning or urgency worsens, symptoms persist, or you feel unwell; ask whether a urine sample should be collected before antibiotics.
- Seek urgent care for fever, chills, flank pain, confusion, inability to pass urine, or heavy bleeding with clots.
- Never stop, restart, or change an anticoagulant or antiplatelet medicine without explicit instructions. The bleeding risk must be balanced against the risk of stroke, heart attack, or a clot.
- Keep follow-up appointments so clinicians can check healing, urine flow, residual urine, and culture results.
Surgery can improve emptying when obstruction caused infections and residual urine. It cannot guarantee that every future UTI will stop, particularly when another source remains.
Frequently asked questions
When do repeated urinary infections point to a prostate problem?
In men, recurrent infections point toward a prostate or bladder-emptying problem when urine remains after urination, the stream is weak, or symptoms include straining, urgency, and incomplete emptying. Two symptomatic, culture-confirmed infections within six months or three within 12 months meet the usual recurrent-UTI definition.
Which tests show whether the prostate is causing recurrent infections?
Urine culture identifies the bacteria and antibiotic sensitivity. Uroflowmetry measures urine flow, ultrasound measures prostate and bladder findings, and a post-void residual scan shows how much urine remains after urination. A urologist may also use cystoscopy or prostate imaging when the diagnosis remains unclear.
When can laser surgery reduce the risk of another urinary infection?
Laser surgery can reduce risk when benign prostate enlargement blocks urine flow and leaves significant residual urine that repeatedly becomes infected. It does not prevent infections caused by stones, resistant bacteria, sexually transmitted infections, or another untreated urinary abnormality.
What changes when chronic bacterial prostatitis is suspected?
Chronic bacterial prostatitis requires a culture-guided treatment plan because bacteria can persist inside prostate tissue. A urologist may compare urine samples before and after prostate examination and investigate stones, obstruction, or other sources before recommending surgery.
How should you manage recovery and a urinary infection after prostate surgery?
Follow catheter, fluid, activity, and medication instructions from your surgical team. Burning and blood-tinged urine can occur during early recovery, but fever, chills, worsening pain, confusion, inability to pass urine, or foul-smelling urine needs prompt medical assessment and a urine culture.